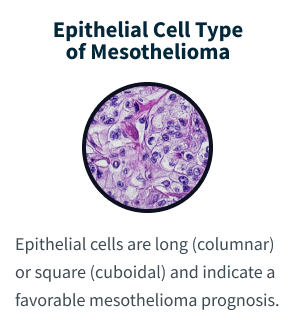
Epithelioid mesothelioma is the most common subtype of malignant mesothelioma, accounting for 50% to 70% of all cases. Caused by asbestos exposure, it has the best prognosis and most treatment options of all mesothelioma cell types.
Learn more about mesothelioma, asbestos and the steps you can take to fight this disease.
Epithelial mesothelioma is an aggressive form of mesothelioma cancer that develops on the tissue that lines the organs of your body. This membrane, called the mesothelium, is made of cells like epithelial cells. Inhaled asbestos fibers can get stuck in that membrane and cause irritation that changes the DNA of the cells, making them cancerous.
Pathologists look at tumor and tissue samples and determine what cells they can see. If the majority of cells from your mesothelioma sample are epithelioid cells, your mesothelioma subtype is determined to be epithelioid mesothelioma.
“Epithelioid” and “epithelial” are sometimes used in ways that feel interchangeable. But epithelial cells are normal cells that line the skin and the inside of organs. Epithelioid cells can be found in both cancerous and non-cancerous conditions. Epithelioid cells look like epithelial cells, which are shaped like columns or cubes. However, epithelioid cells may come from different types of cells that have mutated or changed shape, taking on an appearance similar to epithelial cells.
The epithelioid subtype of mesothelioma has a more favorable prognosis. Epithelioid cells respond better to aggressive treatment than sarcomatoid cells. Having a combination of epithelioid and sarcomatoid cells is called biphasic mesothelioma. People with this subtype benefit if they have more epithelioid than sarcomatoid cells.
“The survival rate for epithelial patients is overall significantly longer. Epithelial cell type is the best mesothelioma cell type to have. This patient will have more options, such as surgery, and is more likely to respond to treatment.”
Karen Selby, registered nurse and Patient Advocate at The Mesothelioma Center
“Epithelial subtype mesothelioma describes the type of cells the pathologist is seeing under the microscope when they look at a patient's tumor. The epithelial type does tend to be more favorable. It does tend to respond to chemotherapy a little more easily, but it also can metastasize or spread to other places such as the lymph nodes or other organs.”
Dr. Andrea Wolf, director of the Women’s Lung Cancer Program at Mount Sinai
“For nearly a year I was diagnosed as having pleurisy and pneumonia. I soon realised something wasn’t right… Eventually, after lots of tests …the result of the biopsy was mesothelioma. I even thought they had made a mistake and the doctor was also shocked… he asked me if I had worked in the shipyards. My father mixed asbestos cement at his work. He would come home in his overalls… He would lift my brother and me up when coming in from work to greet us.”
Christine S., epithelial mesothelioma survivor
Epithelioid cells make up 60% to 70% of mesothelioma cases, which is more than any other cell type.
Doctors diagnose 1,500 to 2,100 patients with epithelioid mesothelioma annually.
Epithelioid cells comprise about 75% of peritoneal mesothelioma tumors.
The epithelioid type has the best prognosis of all mesothelioma subtypes.
Average life expectancy with surgery is approximately 18 months.
The latency period is 20 to 60 years after initial asbestos exposure.
Epithelioid Mesothelioma Symptoms
Epithelioid mesothelioma symptoms often include cough, shortness of breath and lack of appetite. Symptoms can depend on where on the mesothelium the cancer develops: the lining of the lungs (pleura), abdomen (peritoneum), heart (pericardium) or testes (tunica vaginalis).
Common Symptoms of Epithelioid Mesothelioma
Abdominal pain or bloating
Ascites or fluid buildup in the belly (peritoneal effusion)
Bowel or bladder changes
Chest tightness or pain
Cough, hoarseness or difficulty swallowing
Difficulty breathing
Fatigue
Fever or night sweats
Fluid buildup in the chest (pleural effusion)
Loss of appetite
Nausea, vomiting or diarrhea
Shortness of breath
Unexplained weight loss
Studies show early symptoms may be mild, making it difficult to diagnose. Late diagnosis can cause delays in treatment. As the disease progresses and tumors increase in size and spread, more severe symptoms may appear.
Mesothelioma cancer symptoms are the same, no matter the cell type. But the cell type affects which treatments are most helpful. Talk to your doctor if you experience any of these symptoms.
Surviving Mesothelioma Book
A Survivor’s Guide to Living With Mesothelioma
Learn about Judy Glezinski’s inspiring journey as a mesothelioma survivor, and get tips on how to improve your prognosis.
The primary risk factor and cause of epithelioid mesothelioma is asbestos exposure. This is true for other types of mesothelioma as well. Inhaling or swallowing asbestos fibers causes inflammation and DNA damage. This can lead to cancer many years later.
People are commonly exposed to asbestos at work, in the environment, from contaminated talc or damaged asbestos products in homes, schools or other older buildings. Not everyone exposed to asbestos develops mesothelioma, though there is no safe amount of exposure. Additional risk factors can include the amount and length of exposure and possible genetic predispositions for developing cancer.
Many people with epithelioid mesothelioma worked with asbestos products years before their diagnosis. All mesothelioma cell types have a latency period of 20 to 60 years. The first symptoms may not appear for decades after the initial asbestos exposure.
Christine S.
Verified Asbestos.com Survivor
Survivor Faces Malignant Epithelial Mesothelioma
Christine S. was diagnosed with epithelial mesothelioma after nearly a year of unanswered questions and pleurisy and pneumonia misdiagnoses. She remained resilient through 6 intense rounds of chemo. Today, she shares her experience to raise awareness about the risks of secondary asbestos exposure and advocate for earlier diagnosis of mesothelioma.
A tissue biopsy is the only way to diagnose epithelioid mesothelioma. This procedure involves taking samples of suspicious tissue. Pathologists examine the tissue samples under a microscope to identify specific cell characteristics.
Epithelioid mesothelioma cells clump together in groups and don’t tend to travel. These cell types are less likely to spread to other areas of the body. When a pathologist confirms the presence of specific cancer cells, an accurate diagnosis of your mesothelioma type can be made.
Your mesothelioma doctor will review your detailed personal pathology report that describes the types of mesothelioma cells found. You and your doctor will discuss the types of treatments that typically work best for epithelioid mesothelioma, your overall health and goals to determine which therapy options may be best for you.
Exclusive Content
Dr. Jacques Fontaine: Mesothelioma Pathology Expertise Matters for Diagnosis
Diagnosing mesothelioma is difficult.
Mesothelioma usually presents in the chest with fluid around the lungs.
It presents with pain. It presents with plaques seen on an x-ray or a CT scan. However, there are multiple, much more common reasons to have fluid around the lung or plaques on the chest. They’re not necessarily mesothelioma. And that’s why a diagnosis of mesothelioma can take months. The best way to diagnose mesothelioma is to actually take a biopsy, a small piece of it, and look at it under a microscope.
And not just look at under a microscope by any pathologist, but pathologist who has an expertise in making that diagnosis. Because even with a good sample of tumor, looking at it under a microscope, it can sometimes be difficult to make that diagnosis.
And it’s important not only to know that it’s mesothelioma, it’s important to know what is the histological subtype. Is it epithelial or is it sarcomatoid or is it a mixture of both called mixed or biphasic? Does that change the type of treatment? But in these days, that’s not enough.
We need to know what is the genetic fingerprint of that tumor. What are some of the proteins that are overexpressed on that tumor? What are some of the driver mutations, the genetic alterations on that tumor? Because now we have specific cancer medications for each one of these mutations, for each one of these these proteins.
So it’s personalized medicine, individualized treatment for individualized cancers. We can no longer treat all cancers the same way. Just like there’s no two people that are identical, there are no two cancers that are identical. The ability to choose the right treatment for the right patient will decrease the likelihood a patient will get side effects, will increase the likelihood that a patient responds to the treatment that the tumor shrinks or the tumor gets cured.
So knowing more about the tumor will allow us to find the right treatment for that tumor.
Diagnosing Epithelial Mesothelioma With Immunohistochemistry
The tool or technique for studying cancer tissues is called immunohistochemistry. Pathologists look at stained samples, testing for certain proteins linked to epithelial cells. If pathologists find proteins from other cancers, they’ll rule out epithelioid mesothelioma. An official diagnosis also depends on the tumor’s appearance, location and cell traits.
Immunohistochemistry Markers
Marker
What It Helps Confirm
Calretinin
Present in mesothelioma cells, especially sarcomatoid cells
Cytokeratin 5/6
Found in more than 75% of mesothelioma cases
Podoplanin (D2-40)
Distinguishes mesothelioma from adenocarcinoma
WT-1 protein
Helps confirm pleural mesothelioma
Subtypes of Epithelial Mesothelioma Cells
While epithelioid is a subtype of mesothelioma, there are further subtypes of the epithelioid type. Pathologists can identify these cell subtypes with immunohistochemistry.
Epithelioid mesothelioma has a better prognosis than other subtypes, but some epithelioid cell subtypes also have better prognoses than others. For example, adenomatoid cells are associated with a better mesothelioma survival rate.
Patient Advocate Danielle DiPietro explains why it’s so important to diagnose your cell subtypes. Danielle tells us, “When I speak with a patient who is hesitant to have a biopsy, which is rare, I explain that diagnosing the cell type is imperative for assessing treatment options.”
Epithelioid Cell Subtypes
Subtype
Key Trait
Prognosis Note
Adenomatoid
Also called the microglandular type; makes up only 6% of pleural cases
The peritoneal form behaves like benign lesions and responds well to treatment
Deciduoid
Very rare, with fewer than 50 diagnosed cases; most often affects young women; more common in the abdomen than the pleura
Can be mistaken for other cancers, including a lung cancer called squamous cell
Glandular
Often develops in the pleura, with patterns that resemble glands
Behaves like adenocarcinoma that has spread to the pleura
Small Cell
Doesn’t show the stream, ribbon or rosette patterns found in small cell lung cancer; occurs more often in the abdomen
Median survival rate is around 8 months
Solid
Well-differentiated cells group in nests, cords or sheets and resemble noncancerous growth
Poorly differentiated cells may look like large cell carcinoma or lymphoma
Tubulopapillary
A common subtype that can resemble adenocarcinoma of the pleura
Distinct from benign well-differentiated papillary mesothelioma
Well-Differentiated Papillary Mesothelioma
Rare subtype often found in young women with no history of asbestos exposure
Less likely to spread or cause serious harm than other mesothelioma types
Adenomatoid
Also known as the microglandular cell type, this accounts for only 6% of pleural cases. The peritoneal form behaves like benign lesions and responds well to treatment.
Deciduoid
Doctors have diagnosed fewer than 50 cases of this very rare subtype. It most often affects young women. Just more than 50% of deciduoid cases occur in the abdomen, and less than 50% occur in the pleura. It can be mistaken for other cancers, including a type of lung cancer known as squamous cell.
Glandular
Glandular tumors often develop in the pleura and have patterns that resemble glands. These cells behave like a type of cancer called adenocarcinoma that has spread to the pleura.
Small Cell
Small cell mesothelioma doesn’t show the patterns found in small cell lung cancer. Those patterns include stream, ribbon or rosette. This cell type occurs with greater frequency in the abdomen. The survival rate is around 8 months.
Solid
Well-differentiated solid cells group in nests, cords or sheets. They resemble noncancerous abnormal cell growth. Poorly differentiated cells may look like large cell carcinoma or lymphoma.
Tubulopapillary
This common epithelial subtype can resemble a cancer called adenocarcinoma of the pleura. It’s not the same as benign well-differentiated papillary mesothelioma.
Well-Differentiated Papillary Mesothelioma
WDPM is a rare subtype of mesothelioma often found in young women with no history of asbestos exposure. It’s also less likely to spread or cause significant harm compared to other types of mesothelioma.
How Is Epithelioid Mesothelioma Treated?
Doctors often use a mix of treatment options like chemotherapy, immunotherapy and surgery to treat epithelioid mesothelioma. Using different therapies together can help patients live longer.
People diagnosed in early stages usually undergo aggressive treatment, while those with late-stage cancer often opt for palliative care, which may include immunotherapy, chemo and Tumor Treating Fields. However, palliative care can be helpful at any stage to manage symptoms and improve quality of life.
Common Epithelioid Mesothelioma Treatments
Chemo:Chemo drugs penetrate and attack mesothelioma cells, either destroying them or preventing their spread. This treatment can triple the mesothelioma survival rate.
Combinationtherapy: Mixing treatment approaches, or multimodal therapy, integrates multiple mesothelioma treatments to fight cancer from different angles.
Radiation:Ionizing radiation, including high-energy X-rays or particles, is used to destroy cancer cells. This helps shrink tumors, relieve pain and reduce the risk of recurrence and spread.
Surgery: Procedures like extrapleural pneumonectomy or EPP and pleurectomy with decortication P/D are common surgeries for pleural mesothelioma. Tumor-removing surgery such as cytoreduction with hyperthermic intraperitoneal chemotherapy, known as HIPEC, is used for peritoneal mesothelioma.
The epithelioid cell type responds better to surgery and chemo than sarcomatoid or biphasic mesothelioma, affording mesothelioma patients more multimodal therapy options. As Dr. Jacques Fontaine, thoracic surgeon and director of the Mesothelioma Treatment and Research Institute at Moffitt Cancer Center, tells us: “Usually epithelial type is a slightly less aggressive type of tumor. And usually it responds fairly well to chemotherapy. It may even respond to immune therapy. Surgery may be an option in epithelial type mesothelioma in specific circumstances.”
Patient Advocates can connect you to experienced mesothelioma specialists at top cancer centers who can provide additional insights or offer different treatment choices. Patient Advocates or your healthcare team can also help you find clinical trials that test new therapies or improvements to standard treatments.
Our Exclusive Pleural Mesothelioma Surgery Panel
Medical Outreach Director Missy Peterson discusses surgery for pleural mesothelioma with thoracic surgeon Dr. Raja Flores of Mount Sinai Medical Center in New York City and Dr. Marcelo DaSilva of AdventHealth Orlando.
Exclusive Surgeons Panel
Drs. Raja Flores and Marcelo DaSilva: Mesothelioma surgeons discuss the benefits of mesothelioma surgery in our exclusive panel.
Welcome to our first ever panel. We’re trying to educate patients on the benefits of surgery for pleural mesothelioma. So we wanted to welcome you both. We have Doctor. DeSilva from AdventHealth and Doctor. Flores from Mount Sinai. Thank you both for being here.
Thanks for having us. Thank you. It’s a pleasure.
So we’ll just hop into surgery questions. So a lot of patients who come to us want to know like how are surgery decisions made? Like how do you determine whether somebody is an eligible candidate for surgery?
So when a patient comes to see me frequently they think oh I’m going to see a surgeon that means I need surgery. Half the patients I see I don’t operate on. Half the patients I see I don’t think are good candidates for surgery.
How do I figure it out? First, you’ve to get to know your patient. You’ve got to find out what motivates them. What are they willing to do?
How much are they willing to endure as far as treatment is concerned? Surgery is a big deal, especially for mesothelioma. You make a big cut in their side, you go in there, you spread the ribs, and you’re trying to get out as much tumor or all the tumor that you can. Not everybody is going to tolerate that.
I think it’s really a combination of factors, not only one single factor. Is their health status, adequate to go, not only through surgery, but as we know through chemotherapy, but specifically through surgery. They have a good functional status and we have ways to measure that. Do they have family support as well?
Because it is a process, it’s just not one stop and go, it’s a process of treatment that we have. So those are the things that we take in consideration. What is the stage of the disease? Is the stage advanced enough that even with surgery, we would be able to help those patients making surgery not only ineffective but not indicated.
So those are the factors that we tend to look. Overall, there’s so many things that goes into it, but just the first, we usually call it the eyeball test. The patient comes in walking, talking, and explaining to us his journey about the disease process, then we know they probably would do well. That’s pretty much what we first encounter with the patient.
If you’re older, if you’re weak, if you have a lot of medical problems, if you’re short of breath and you have trouble walking, we get these pulmonary tests to make sure that their lung function is good. We do a cardiac test to make sure they’re okay. And then, like Marcelo said, you’ve got to pass the eyeball test. A surgeon, when they look at you, they know whether or not you’re going to be able to tolerate surgery or not.
So for example, I use Lance Armstrong. I say, how did he beat cancer? Now, he had a different type of cancer, but he was strong enough where he could tolerate getting surgery, getting chemo, getting radiation. You were able to throw the kitchen sink at him.
So when you have a patient, you can’t just see mesothelioma. You need to see that mesothelioma in the context of that patient that’s in front of you. And like I said, half the patients I see, I do not offer surgery to.
Yeah, it’s very interesting you say that because I had the pleasure of meeting the late David Sugarbaker and his whole thing was attitude is everything. So like if a patient would come in and see him for a surgical consult, if he didn’t feel like they could beat it mentally in their mind, he wouldn’t even offer surgery.
There’s truth to that. Yes, that is exactly right. And we both trained under Doctor. Sugarbaker and we’ve learned so much from those years, those years of what I call seminal years in which we’re all learning how to move forward with our patients. And yes, I think a mental attitude is almost not everything, but a lot goes into it. You know, we used to say, you know, when patients get the diagnosis in pathology of mesothelioma, it’s like reading a death sentence. That’s the feeling the patients have.
Right.
And we as providers, whether it’s a surgeon or medical oncologist, I think part of our job is to bring hope to that patient. Take that idea that it’s a death sentence. And I usually say look people live with breast cancer, colon cancer, prostate cancer for years. We can’t control your pro You’re not going to die tomorrow. We all have an expiration date, but let’s just put that aside. Let’s think about how we’re going to treat you in your journey through this treatment, long treatment arm that is. But those are the things that we looked at, but yes, you’re right, I’m mentally prepared.
There’s a lot to be said about that. But you hit the nail right on the head. Mesothelioma is not a death sentence. That’s a very important thing that patients have to take away when they visit a doctor because on the internet it paints a different picture.
Sure does.
First thing I do when I have a mesothelioma patient who’s seeing me, I get my other mesothelioma patients who are alive five, ten years later and I put them together. And I say, Can you guys talk? Yeah. And so that is the best thing that a patient can have, is that person in front of you who’s already had the diagnosis, who’s went through surgery and all the other stuff still sitting there ten years later. Right. And that’s the single most important thing you can give that patient is hope.
I agree.
So we’ll move on to the next question. They want to kind of know about the guidelines, cell type, stage, disease distribution, overall health, and responsive treatment for patients when you’re determining if they’re a surgical candidate.
So there’s not one thing that’s going to rule you out from surgery.
You know, having certain things are favorable. Epithelioid, good performance status, localized disease, not a lot of bulk of disease, a lot of volume. But like I said, it depends on the patient. You may see a patient who’s an elderly patient, let’s say 80 years old, has a little trouble walking, you’re concerned about them recovering from surgery and they have a sarcomatoid tumor, do they have positive lymph nodes? Those things may steer you away from surgery. Now you’ve got a young patient, 40 year old mother has two kids.
She’s willing to just fight to the end with this. And you realize, okay, she’s epithelioid, it’s localized in that chest.
Maybe she has diabetes or something else, which is a little negative.
But you’re like, Okay, we’re going for it. And you just got to feel like you’re in that fight with that patient.
But it’s not one size fits all. You have to tailor it to whoever’s in front of you. Right.
Yes, that’s exactly right. I mean, again, there’s many type of cells, different cells, 80 total of type of histologic different mesothelioma cells because it’s such a diverse group of cells that can grow in different As a matter of fact, forty percent of patients who had their specimen removed in leukemopathology, forty percent of them have mixed cells. In other words, they may be predominantly epithelializing, that’s what we like to see. But there are also other elements of different cell types that will be present in that tumour.
But having said that, mean it’s like Roger said, it’s all those things that can influence our decision to operate in patients. Usually we say, you know there’s a black forest in front of you and if you heard that before it’s alright. You don’t know how to navigate, it’s dark, it’s black, it’s difficult, it’s scary really. We’ve been doing this for more than twenty five years, we have the road map.
We can say let’s guide you and your family.
Thank you. What are the biggest factors that can make surgery the right or wrong choice for a patient?
Yeah, I think the best patient for surgery is a patient that’s in good shape with tumor localized in that chest.
The patient that’s not the best candidate for surgery is somebody that has spread to the other chest or in the abdomen.
Those are the patients that are not best suited to have surgery. So localized, and they can handle the surgery, I think that’s in their best interest. I think that will get rid of more tumor than if you’re just given chemo, than if you’re just given radiation. It’s a guaranteed response. You’re getting all that tumor out.
I’m biased as a surgeon but I’ve been doing this for thirty years.
That’s where I see the long term survivors. I think it’s important when patients are considered for surgery to go to a specialized center.
The centers that across the country there are many that are used to taking care of patients. Again it’s just not the surgical act in itself. It’s the whole process, the family process, the nutrition status, rehab, prehab. Go to a center in which, surgeons are used to not only doing the biopsy but used to doing the surgery itself.
Whether it’s a pleurrectomy or decortication, but surgeons that are used to deal with the disease process for many years. A lot of times we have patients who come with a biopsy and a surgeon who never seen a mesothelioma patient before in their lifetime, because it’s such a rare disease. Nothing wrong with that, but go look for a second opinion. Go to a center in which people can offer you a whole gamut of treatment.
Right.
One thing I love about referring patients to both of you for surgical consults is everybody says how caring you guys are and that you actually take the time to listen to them. And not only that, the people who get surgery, like your post op care, is top notch. And I think people don’t realize that that’s why it’s so important to go to a center of excellence like where both of you work because you guys are brilliant surgeons, but you need the team to follow-up with the care to make sure that they get up and get walking and use their oxygen tank because recovery starts with the patient and they have to walk, get moving again, get some fresh oxygen to the lungs. So do you guys feel that that’s one thing that patients should really do is look at using a center of excellence so they do have that post operative care.
What’s interesting is even patients that we don’t operate on, so I’ve got a number of patients from Ohio, from Michigan, they still send me their scans two, three years later and this is without surgery.
Right.
And you know they’re like how about now, should I have surgery? So even though you may not be a candidate for surgery at that point, you never know, two, three years later maybe there’s something somewhere that you may need to take out. And even if not, you help guide them. Listen, I think this immunotherapy just came out. This is in your best interest. For this, I would use radiation.
So any meso patient, in my opinion, is an opportunity to learn from. Whether or not you operate or not, you follow their course to see what helps and what doesn’t help.
A lot of times patients are told they have like twelve months to live. So it’s interesting that you say that you have patients who come back to you like a year, two years after they got their diagnosis. They never had surgery. They’re realizing, oh my gosh, I’m living. So now maybe I should look into surgery. So I find that very fascinating that like patients after they get over the initial shock of having the diagnosis, they do well on chemo or immuno, and then now they want surgery. So how do you guys handle that portion of it?
I mean, really depends on the patient. Not everybody is going to live past that twelve months and that’s a reality we have to face as doctors and as patients. So there are patients that will be dead within twelve months. The question is how do you figure out who’s the best candidate for surgery?
So you have some patients who have disease, they’re going to die no matter what you do. You have some patients who have disease, they’re going to live no matter what you do. And then you have this group in the middle where the tumor is expanding and it’s trying to do something bad and it’s a situation where you can intervene as a surgeon. Where what you do today can change what happens tomorrow.
And those are the groups of patients that you really have to try and figure out. And thirty years later, we’re still not great at it. We’re still trying to figure it out. We’ve used histology, epithelioid, functional status, extent of tumor, volume of tumor.
There’s a number of things and we still figure it out. That’s why any patient that sees me with mesothelioma, I follow them forever, whether they have surgery or not, so that I can learn and figure out what am I going to do with the next patient that comes in and sees me. You’re constantly trying to learn, because the data is very fragmented and it’s not uniform. And so you have to you know, there was a Yankee that used to say common sense ain’t too common.
So you want to use your common sense, which is right in front of you. And then in the end, you just put your own family there and do what you would do with your own family member. In the end, that’s all you can really do as a surgeon.
Yeah, so I actually enjoy that question when it’s posed to us in our clinic. The doctor told me I have twelve months to live. There is the dismal diagnosis, the death sentence, and I really enjoy getting that question because I turn right around and says, you need to go back to that doctor and ask him how long he’s gonna live.
Because if he tells you how long he’s gonna live, I will trust him.
Yeah.
You’re gonna live twelve months.
Right.
Like Roger said, I mean, it’s there’s so many things that goes into it. Yes, we had patients. I had patients with all good performance status, patients 56 within six months of that surgery they’re gone. And I had and I’m a question that I usually ask you know we usually say what’s the what is the oldest patient you operate and how often do you follow? We follow them forever. That’s how we do it.
You have patients who follow you still, I like know, the first wiped day all you’re in over, yes.
They come back and follow. We get to know their families, their dog names, and everything else because they always showed up. Anyways, I usually say, look, we need to take a case by case. I can’t tell you.
Yes, there is an average. If you want to talk scientifically, I’m gonna tell you by the stage, by the type of cells, probably how long you have to live. But that’s a combination of data that it’s all over the place, doesn’t apply specifically to you. So if we think the patient’s gonna live, has a good support and so forth, good epithelioid, good histologic factor then yes, I don’t give them a number because we do have patients seven, ten, twelve, seventeen years out of this disease and still some of them enjoying life fully.
I usually ask you know how old you have to be. I’m afraid to say the oldest one I operated was 82. 97. There we go.
Because you want to go parachuting or something like that. And but then you turn around and say how about the youngest? So there is a really a 26, it doesn’t really it’s it’s an 82 and a 97 says I wanna live. I don’t want this in my body.
And you see them through. It’s it’s it’s a gift of of life that we we bring to the table. But you brought a very interesting point. All of that goes into a great team that we have.
More than twenty, thirty people helping those patients all the time. Not only just once when they come and see you for surgery. It’s a lifespan, it really is. And that’s what makes us so interested in following our patients on Meso Toulioma.
Yeah, I get the pleasure of going to a lot of the conferences, the scientific conferences, and IMEG, they had a whole section on biphasic meso. And I thought that that was really interesting because it looks like that’s gonna be like the new research where they’re gonna narrow down if it’s more epithelial. Those people will start to become surgical candidates, more sarcomatoid, maybe immuno. What do you guys think with the whole biphasic thing? Do you think it’s going to open up opportunities as you guys start seeing the percentage of different cell types?
So the mixed and the sarcomatoid question is an important one because many times people will just automatically say no surgery.
And for many patients surgery is not the right answer. But like I said, when you’re looking at a patient and trying to determine what their treatment should be, whether it’s chemo immunotherapy, radiation, or surgery, you need to put it in context of that particular patient. While most patients with sarcomatoid will not get surgery, are not recommended to get surgery, if I have like I talked about that example of that young woman, if I have a 40 year old male in great shape, it’s localized in that side, and they understand, listen, the results with sarcomatoid aren’t the greatest, but if they want surgery and they understand the risks and benefits with it, I will operate on that patient. And yes, I understand what the data shows. I know what’s out there, but statistics are for patient populations. What you have in front of you is an individual. And as long as they understand what they’re dealing with, I will offer them surgery.
So you believe in patient choice. Like you ultimately, if you feel like they could have some benefit, you give them the option to.
You know, nowadays we talk about this personalized medicine tailored to the particular patient for drugs. Why don’t we do it? Surgery is the natural tailor to that particular patient. So you just have to focus on who’s in front of you. You know, the statistics, I got a master’s in statistics, I get it. But when you got a patient in front of you, that’s a different story.
That’s right, it’s N of one.
Every patient is important. That’s how we see it. That’s what tell the patients. Now as far as biphasic, mixed type, epithelioid, sarcomatoid, think what Doctor. Flores said is exactly right, I take a patient at a time. But the most important thing that I’ve noticed in the office is either to call the medical oncologist to talk with the patient as well and ask them to suspend judgment.
And it’s very difficult as a practitioner. The patient comes in with a diagnosis of, for instance, biphase mixed or even sarcomatoid. So we have this preconceived ideas that this patient might not be the right surgical candidate. To suspend that judgment, that’s all I ask.
Put that on hold. Look at the patient, talk with the patient, see what they want for life. It’s understanding not only the disease process but understanding the patient, him or herself. I think that’s key to treating patients with mesothelioma.
It makes it so special.
Yeah, that’s great. What are the biggest misconceptions you think patients have about surgery?
Well, think patients come to us and they say, Oh, it’s going to hurt. Again, it’s suspended their judgment that surgery is going to make me impaired or paralyzed or something awful. That’s not really true. We’ve come a long ways from I think when we were in training we did maximally invasive surgery all the way to remove almost half of a body really.
Today we tailor that surgery to the patients. We’re less invasive. We’re still taking as much as we can off the tumor because that’s where the money is so to speak. It’s removal of all we can see. That’s the key for survival with surgery. But that’s a misconception, is I’m gonna hurt a lot, I’m gonna be prepared a lot, recovery time is gonna be a long time. Well, yes, so is for other people as well with other diseases.
Again, you have to understand that you’re going through surgery. Some patients, they get up, and we strive for this, get up two days later, they walk in the hallways. I think I have a couple postings showing patients walking with a walker, we call the Brigham Walker. They used to walk around carrying the oxygen and talking to their family members two days after the surgery.
And I think after six weeks, seven weeks, eight weeks, they’re almost back to normal, with the way we do surgery today. I think that’s a big misconception, not only for patients, but for physicians who send the patients to us, Oh, you know, you’re going to have surgery. Instead of, Oh, you’re going to have surgery. You’re a perfect candidate to have a multi modality therapy.
So really it’s a suspension of judgment that we need to understand when patients come to us about surgery.
Yeah, I agree.
Yeah, I think the misconception about surgery is historical. When you look at the surgery for mesothelioma, there are two surgeries. There’s the extrapleural pneumonectomy and the pleurrectomy decortication. The extrapleural pneumonectomy back in the 60s or 70s, there was a paper that came out from England, Buchhardt, which had a mortality of, I think, twenty eight percent, thirty percent mortality, which means that three out of ten patients who had that surgery died. Now that’s a surgery you don’t want to do on anybody, but that’s where I think a lot of this misconception came from. Oh my god, the surgery is so big everybody dies with it, and that’s not true.
Over time, what we started doing was we started doing extra pleural pneumonectomies, is taking out the lung, the pericardium, the lining of the heart, the diaphragm, the lining of the muscle between your chest and abdomen, and taking all that out and we found we can do that surgery with acceptable mortality of less than four percent.
But then everybody has this misconception, oh my god doc you’re going to remove my lung, like that’s a big deal. You know Pope Francis had one lung for his whole life and he’s running around you know preaching. So there’s a lot of misconceptions and then over time we actually did a study comparing extrapleural pneumonectomy to pleurrectomy decortication and found that you have the same outcome but pleurrectomy decortication had half the mortality. The patients did better clinically. So surgery has evolved but this mystery or this specter of surgery being huge and, debilitating, I think came historically. Nowadays the surgery can be done with such great results. Our own study that just came out, we had a zero percent mortality at thirty days.
So this scary thing about surgery just is not true.
If you go to the right center with the right surgeon.
That is correct.
Who actually specializes in meso and does a lot of surgeries like the both of you. Yes. So how has surgery for pleural mesothelioma evolved over the past decade?
I think we’ve learned a lot, all of us, from our own experience and others as well as we go to meetings and talk. It’s a very small community of surgeons who can actually perform an adequate surgery, an effective surgery, with the focus on removal of all we can see. But it has evolved in a way that, for instance, we used to almost always remove one or two ribs, we don’t do that anymore. We used to do a very large incision, we don’t do that anymore. We’re more conservative in the way we attack the tumor.
I think that is a big change. We also have more ways to treat pain, for instance. I use cryoablation, which is one of the modalities to freeze the nerves during the surgery to decrease the amount of pain. But we have epidural catheters, have all the different modalities that really help the patients.
I think we’ve learned and evolved, it’s a good thing to evolve, and learning from our own experience what works and what really doesn’t. We used to remove most all the diaphragms, the breathing muscles, we don’t anymore. We can do a splitting of the diaphragm, we can do patches on it. So there’s different ways that we can do almost the same surgery but be less invasive.
And I think that’s what we’ve learned throughout the last twenty, twenty five years.
Yeah, it’s interesting. It seems like we’ve come full circle. When you look back in the 1930s, it was pleurrectomy that was really the treatment of choice. Then came the 80s and David Sugarbaker, and he really pushed extrapleural pneumonectomy. That’s because he was working with Karen Antman. Antman said, Hey, I need you to get more of this out so I can give certain drugs.
So then extrapleural pneumonectomy evolved. Then from my standpoint, I not only learned from David Sugarbaker, but I also learned from Valerie Ruche and from Harvey Pass. And they were doing more pleurectomies.
And then we compared the results and found that wow, you can get the same results with pleurectomies with less mortality. So then it shifted back to pleurectomy. And I think one of the biggest things that has shifted now is, like Marcelo said, we used to reflexively take the entire pericardium, take the diaphragm. What does that do?
It opens up another cavity and allows meso cells to sneak in there and cause spread as opposed to helping get rid of tumor. And then if you do that in the belly, get seeding of the belly. So we’ve learned you don’t want to seed those other areas. So we’ve went from pleurrectomy in the 1930s to extrapleural pneumonectomy taking out pericardium diaphragm back to pleurectomy, extended pleurectomy and now back to pleurectomy tailored to that patient in front of you which has the best outcome.
That’s excellent.
I do want to just ask because I get this question a lot from ladies. They want to know about the scar because you’ve seen the uptick in women who are now getting this unfortunate diagnosis and they’re all so concerned. I’ve seen the scars myself from some of the ladies who I’ve met along the way, and they’re not as bad as they used to be. So for the ladies out there who are not wanting to do surgery for vanity reasons because they don’t want the scar, can you guys talk a little bit about the scar for them?
Yes, I usually tell them, look it’s going to be on the line of the breast crest. It’s going to be almost in a natural line. And again, we try to really make it as small as we can.
I usually tell the patients I’m not a thoracic surgeon I’m actually a hand surgeon. I operate anything I can put my hand in it. So if my hand fits in there and I can do a dissection that we wanted to do with a small incision that’s what you’re gonna get. But at the end of the day you really have to have a one to one conversation, ask what is that you’re looking for? Is a scar important for you if it is and you are going to have a scar, or is that extension of your life and preservation of your health?
Those are the hard questions that we have to ask the patient sometimes.
Yeah, I don’t sugar coat it.
You’re going to get a big scar.
I think when you limit your insulin, and I’m a minimally invasive guy, Lung cancer, I’m all minimally invasive. But for mesothelioma, you miss stuff if you go in minimally invasive. I have tried to do these operations minimally invasively. It’s just they go around every corner in every crevice, and you really have to work to get those two, not just the cells, but the sheets of tumor that are in there.
And I don’t know of any way robotic that I just don’t think you can get to it.
So I will make an incision. I tell them, You’re going have an incision on your side like that. I’m going go in between your ribs. We don’t take a rib out anymore. And we go in there and we go through those tissue planes. But, you know, if you don’t want to have an incision, then don’t have the surgery. Because the only way I can tell you that I’m going to get out all that tumor is by making a good incision, and by going in every little nook and cranny.
Yeah, that’s a very good point, which is the, and we see this on and off. These patients ask, Oh, I went to see someone else and they said they can do a robotic operation.
They I hear that about do video thoracoscopic operation, so it’s gonna be an incomplete operation.
It’s like anything else and we have to tailor the operation to you and your disease process. And I’m yet to feel happy or satisfied with minimally invasive procedure unless you’re doing a biopsy for diagnosis. Other than, yes that there’s place for that but other than that I think we really need to go back to the surgery that we used to do modified yes and open and open surgery.
Happens is they get minimally invasive and something else like a doc or something that makes our next surgery more difficult. Right. And there’s no treatment reason for that. So that’s what really sometimes it’s confusing to patients is oh I’m gonna get a minimally invasive, you can’t not really get a minimally invasive pleurrectomy decortication.
You just can’t. Adequate. Right. A cancer pleurrectomy decortication.
Yes, different. Many times they do Vance decortication but that is for infection. Yes.
Okay.
Not for cancer. I think people get confused with Correct.
It’s a great point. As far as advances in surgery or perioperative, what do you think the biggest impact that has on patient outcomes?
I think the biggest impact is getting out that cancer. So you have tumor that’s there. You see it on the CAT scan. You see it in the patient when they’re there. You get that out. That starts the time clock back here.
You give chemo, maybe you get a little response. What’s a response? That’s when you get a CAT scan and you may see it a little smaller. There are many different things that can do that.
If you have a different radiologist reading it, If you took a big breath with one scan and not a big breath with another scan. Are you really getting a response? Is that drug really working? From what we know with meso drugs, maybe twenty percent response rate, if you’re lucky.
With surgery, you’re getting a guaranteed response. You’re going in there and you’re getting it out. That’s what you want. What people are worried about, can you recover from surgery?
Yes, you can recover and you can do very well. Hopefully a surgeon’s not going to operate on you unless they can tell that you’re doing very well. Is there a downside to chemo? Yes, people die with chemo.
It’s not like, Oh, you shouldn’t have surgery, you should have chemo, you should have immunotherapy. People get hurt with drugs as well.
You know what we do is we take it out and then we give radiation afterwards to get the microscopic stuff there and Ken Rosenzweig who was with me at Memorial is the guru for doing radiation. So that’s what we do. We do the pleurrectomy and we follow it up with radiation.
What questions do you think patients should ask a surgeon when they’re determining if they should do surgery or not?
I think we probably agree with the same experience.
Have you as a physician, as a surgeon, treated patients with mesothelium? For how long?
Do you offer multi modality treatment? Does your center offer multi modality treatment?
Do you have a team that has or performs prehab and post surgery rehab? Those are the components. It’s really a robust program. And those are the things that patients should be asking. Do you have experience? Have you done enough?
What are your results? Our results are different, not as much as we would have expected, but they’re different because different patients’ population, different disease process, but what are your results, your personal results? Quite often I get, I had my biopsy done by Doctor. Such and such, do you know him or her? I said, I probably do, but I don’t understand, I don’t know if they’ve done enough mesothelioma surgery to recommend those physicians, surgeons. I think asking experience, asking team approach, multi modality treatment, those are the very important questions that they have to ask.
Yeah, I think it’s a fair question to ask a surgeon how many have you done. That’s a very fair question, and it’s important because a lot of mesosurgery isn’t having fantastic skills, these magical hands or this incredible, no, it’s practical. It’s having been there before, this works, this doesn’t. Experience is everything.
I agree.
Yes.
If every newly diagnosed patient could hear one message before making treatment decisions, what would that message be?
I think hope.
Before you decide which path you’re going to go, we would like to say we have hope for you, hope for your treatment, specifically multi modality treatment including surgery. Don’t suspend your judgment, put hope, a message of hope. Where there’s hope anything is possible. So I think bringing that message to our patients it’s important for them to understand that we’re joining them in their journey for treatment. That’s important.
Mesothelioma is not a death sentence. If there’s one message they need to take home from this, mesothelioma is not a death sentence. Sit in my office, talk to some of those patients that are sitting in that waiting room. Now what’s interesting is some patients are very vocal about it, they want to tell the world. And some patients don’t want to.
They’re tired of this cancer, You lose your identity when you have cancer, You especially don’t become Karen anymore, you become Cancer Girl.
You’re not Joseph anymore, you’re Cancer Boy. Everything’s about the cancer. So many times people don’t want to go out and advocate and I get it because it’s a big wait but you come to one of our offices and you sit there in that waiting room you will see a whole community of miso people who are just running around with their boring lives. Yep.
You know that’s a very important point Doctor. Raj brings to the forum which is don’t let the disease define you, who you are and that’s what we’ve seen as great results. Patients know who they are, they know what they want, they’re looking for the expert and sometimes they’ve been denied already treatment and they say I won’t take that no for an answer. I’m gonna go to New York, I’m gonna go someplace else to find someone who will join me.
So I think when the patients get defined by the disease, that’s usually not a good result coming. Most of the patients they come in with a fight in them and that’s so important as well.
Is there anything else you guys want to discuss about surgery before we wrap up this last portion of the panel?
Yes, I usually tell the patients not to have ants. You know little ants little animals but ants stands for you, we probably heard this before, negative thoughts they crawl up in your mind like little ants and they drive you insane and your family insane and your community insane. No ants. Get the ants out of your mind, positive attitude. Let’s do this together. And it’s it works. I think there’s a chance to do something awesome along with someone that I’m about to meet and bring them that hope.
Yeah, it’s confusing. There’s a lot of information out there. Doctors are confused, Mesothelioma specialists are confused. I can imagine being a patient with all this data out there, all the controversy, all the contrary views.
There’s no right answer. As a patient, when you’re faced with this, you just got to find one person that you trust. Be informed. See multiple different people. Get that second, get that third opinion. But ultimately, listen to that person that you trust and let them guide you because it’s very difficult for you to dictate your own care for something that many doctors don’t even understand.
Perfect. Here’s another one before we finish.
Yes, of course.
So patients come with a pile of information, right? They print it out whatever Yes. Chat they And and they are telling you this and that and the other. And I usually say, when you get in a plane, do you go to the pilot and says, read all about your plane.
I read all about your flight plan to to Orlando or New York. Let me tell you how you’re gonna fly. Or do you just sit there, relax, and say, I’ve gotta trust him. He’s going to school.
He’s got many hours of flying. Right? Someone landed a plane in Hudson. Everyone survived.
Oh, I was there.
It’s going. Right?
Do you go to that pilot and says, Oh, let me tell you how you’re gonna fly. Don’t. Just relax. Trust the provider.
Ask the experience. Ask how many years. Those are the right questions. And forget about all this pilot, cause like Doctor.
Flores said, it adds to the confusion, and that’s just not helping anyone, including the patients.
And you guys are like the first class tickets, so with your expertise.
I’m not sure about that, but we know how to fly the plane, now let’s put it that way. Perfect.
Yeah, mean the one thing to understand about mesothelioma, it’s very humbling. Whether you’re a provider or a patient in their family, there are things that we can do where we’ve seen great long term results, but there are many patients that we lose despite treating them with all this. And so it’s very hard to maneuver. It’s a very, very humbling field.
Thank you both for being here today.
You’re welcome. My pleasure. Thank you.
FREE MESOTHELIOMA GUIDE
Expert Guidance for Your Mesothelioma Journey
Get answers about treatment, top doctors, and financial support from the nation’s most trusted mesothelioma resource.
Epithelial Mesothelioma Life Expectancy and Prognosis
Epithelioid mesothelioma has the most favorable prognosis of the three mesothelioma cell types because epithelioid cells respond better to treatment and spread more slowly than sarcomatoid or biphasic cells. Epithelioid Patients typically survive between 1.5 and 6.5 years, depending on where the tumor develops, the stage at diagnosis and how well treatment works.
People with pleural epithelioid mesothelioma who undergo surgery live an average of 18 months. People with peritoneal epithelioid mesothelioma have a median life expectancy of nearly 5 years. Another study on peritoneal mesothelioma found that people with epithelioid cells lived a median of about 5 years.
Median survival, Imfinzi (durvalumab) plus chemotherapy
24.3 months
Epithelioid patients (9.2 months for nonepithelioid)
PrE0505 trial
Median survival
About 5 years
Peritoneal epithelioid mesothelioma
Peer-reviewed peritoneal mesothelioma studies
Common Questions About Epithelioid Mesothelioma
Where can I get treatment for epithelial cell mesothelioma?
Look for mesothelioma specialists with years of experience treating peritoneal and pleural mesothelioma. Oncologists need training to treat epithelioid mesothelioma, and our Patient Advocates can help you find a top doctor.
Is epithelioid mesothelioma curable?
Epithelioid mesothelioma has no cure, but patients with this cell subtype have the most treatment options and respond best to all forms of treatment.
Is there any ongoing research on epithelioid mesothelioma?
Researchers are constantly looking for mesothelioma patients with the epithelioid cell type for clinical trials. As of May 2026, clinical trials are actively recruiting mesothelioma patients across the U.S. Studying epithelioid patients lets researchers learn how a drug or therapy affects most people diagnosed with mesothelioma. For example, a clinical trial completed in 2024 examined the effectiveness of Itraconazole and Rifampin on epithelioid mesothelioma patients. Final results haven’t been published.
How is epithelioid mesothelioma different from sarcomatoid mesothelioma?
Epithelioid mesothelioma differs from sarcomatoid mesothelioma in cell shape, growth pattern and treatment response. Epithelioid cells cluster together and spread more slowly, giving patients more treatment options and a more favorable prognosis. Sarcomatoid cells have a spindle shape, grow more aggressively and respond less well to chemotherapy. Doctors call a mix of both biphasic mesothelioma.
What are the subtypes of epithelioid mesothelioma?
Epithelioid mesothelioma includes 7 recognized subtypes: adenomatoid, deciduoid, glandular, small cell, solid, tubulopapillary and well-differentiated papillary mesothelioma. Each subtype has a distinct cell appearance under a microscope. Some subtypes, like adenomatoid, have a more favorable survival rate. Well-differentiated papillary mesothelioma is rare and typically less aggressive.
Is epithelioid mesothelioma lung cancer?
No, epithelioid mesothelioma isn’t lung cancer. It’s a cancer of the mesothelium, the thin lining around the lungs, abdomen, heart or testes. Lung cancer starts in the lung tissue itself. Both cancers can be caused by asbestos exposure, which is why people sometimes confuse them.
Recommended Reading
Your web browser is no longer supported by Microsoft. Update your browser for more security, speed and compatibility.
If you are looking for mesothelioma support, please contact our Patient Advocates at (855) 404-4592
Fact Checked
Our fact-checking process begins with a thorough review of all sources to ensure they are high quality. Then we cross-check the facts with original medical or scientific reports published by those sources, or we validate the facts with reputable news organizations, medical and scientific experts and other health experts. Each page includes all sources for full transparency.
Reviewed
Asbestos.com is the nation’s most trusted mesothelioma resource
The Mesothelioma Center at Asbestos.com has provided patients and their loved ones the most updated and reliable information on mesothelioma and asbestos exposure since 2006.
Our team of Patient Advocates includes a medical doctor, a registered nurse, health services administrators, veterans, VA-accredited Claims Agents, an oncology patient navigator and hospice care expert. Their combined expertise means we help any mesothelioma patient or loved one through every step of their cancer journey.
More than 30 contributors, including mesothelioma doctors, survivors, health care professionals and other experts, have peer-reviewed our website and written unique research-driven articles to ensure you get the highest-quality medical and health information.
About The Mesothelioma Center at Asbestos.com
Assisting mesothelioma patients and their loved ones since 2006.
Helps more than 50% of mesothelioma patients diagnosed annually in the U.S.
A+ rating from the Better Business Bureau.
5-star reviewed mesothelioma and support organization.
My family has only the highest compliment for the assistance and support that we received from The Mesothelioma Center. This is a staff of compassionate and knowledgeable individuals who respect what your family is experiencing and who go the extra mile to make an unfortunate diagnosis less stressful. Information and assistance were provided by The Mesothelioma Center at no cost to our family.
Asbestos.com. (2026, October 6). Epithelioid Mesothelioma. Retrieved October 8, 2026, from https://www.asbestos.com/mesothelioma/malignant/epithelial/
MLA
"Epithelioid Mesothelioma." Asbestos.com, 6 Oct 2026, https://www.asbestos.com/mesothelioma/malignant/epithelial/.
Chicago
Asbestos.com. "Epithelioid Mesothelioma." Last modified October 6, 2026. https://www.asbestos.com/mesothelioma/malignant/epithelial/.
Words can not express how grateful and thankful we are to the Mesothelioma Center and their employees. My fiancee who is a 46 year old United States Marine Corp Veteran was diagnosed with Epithelialoid Mesothelioma back on October 2, 2024. To say his diagnosis was a shock would be an understatement. I reached out to the center and reached a message back almost immediately by an amazing woman named Karen. She is there every step of the way with any questions or support that we need. Placing in count with our team has been a God send. Putting us in contact with Aaron and also with Curtis was nothing short of a miracle. Karen and Curtis will always respond to my text messages. We have attempted to go through Veteran Affairs, but we have gotten no help and no response or waiting to speak to someone and being in hold for hours. My fiancee has been fighting the VA for years, only to be given the run around. My fiancee's primary job was 6093 Aircraft Metalsmith you would think that the VA would be the ones to give our Veterans the respect they have earned and deserve, however they give them nothing. Karen and her team have been there for us since we originally reached out. To the Families of Mesothelioma Patients and Mesothelioma Patients; I know the confusion, pain, denial, anger, guilt and sadness you are all facing. If you need someone to talk to, someone who cares about you and your life, seeking justice for all of you for what your diagnosis has done to you on all levels. Reach out to the Mesothelioma Center, we are our loved ones biggest advocate as well as our own reach out for help and support to this amazing group of people. The information they share is beyond helpful and something I was told by Curtis. No small amount of asbestos is too small. The changes your life from the first day of your exposure. If you worked your ass off or served your country and you have been diagnosed with Mesothelioma.. Call this center, and speak to someone who is only a text message away. Thank you Karen you have no idea the impact you have made to Dennis and I. Thank you for being there for us, for that you have already done and for what you continue to do. You are so appreciated
Thank-you The Mesothelioma Center for your help. You were on top of it. The Dr. I wanted a appointment with did in fact call me. I have a appointment I'm so happy. Thanks to Karen
Dr Smart has been a wonderful help to us. She has guided us to the health care providers that are the right fit for my husband’s particular type of cancer. She is also a very caring person and has been there to listen and guide us. We thank her for all her help.
Dr. Jacques Fontaine is a thoracic surgeon at Moffitt Cancer Center in Tampa, Florida, where he heads up the Mesothelioma Research and Treatment Center. He specializes in minimally invasive robotic surgery and aggressive surgeries for mesothelioma.
Fact-checked and verified content:
Our fact-checking process begins with a thorough review of all sources to ensure they are high quality. Then we cross-check the facts with original medical or scientific reports published by those sources, or we validate the facts with reputable news organizations, medical and scientific experts and other health experts. Each page includes all sources for full transparency.
Please read our editorial guidelines to learn more about our content creation and review process.